



Can Trichotillomania Cause Permanent Hair Loss?
Trichotillomania is more than a habit—it’s a powerful, often overwhelming urge to pull out your own hair. For many, it starts quietly: a moment of tension, a search for the “right” strand, a quick pull. But over time, it can become a cycle that feels difficult to control and even harder to explain.
For those navigating trichotillomania Boston, this experience can feel especially isolating. This hair-pulling disorder can affect the scalp, eyebrows, eyelashes, and other areas of the body, often leading to visible hair loss that feels deeply personal. Beyond appearance, trichotillomania can impact confidence, daily routines, and emotional well-being—especially when the cycle repeats over months or years.
Many people describe a familiar pattern: tension builds, pulling provides brief relief, and then feelings like frustration, guilt, or shame follow. Understanding this cycle is an important first step toward change.
At Noelle Salon, our team supports individuals navigating trichotillomania hair loss through compassionate consultations, scalp-conscious solutions, and personalized hair recovery strategies.
While the experience can feel isolating, trichotillomania is treatable. With the right support, strategies, and consistent practice, many people are able to reduce pulling, protect their hair, and regain a sense of control.

Understanding Trichotillomania
Trichotillomania is a diagnosable mental health condition within the spectrum of obsessive-compulsive and related disorders. It involves recurrent hair pulling that the person feels driven to perform, often followed by attempts to stop that are difficult to maintain. For some, pulling is automatic, happening while reading, studying, or watching TV without full awareness. For others, pulling is more focused and intentional, targeting hairs that “feel wrong,” seem coarse, or create an uncomfortable sensation on the scalp or skin.
Triggers vary. Stress, anxiety, boredom, restlessness, and the need for sensory input can all play a role. Some people seek relief from internal tension; others feel compelled by the tactile feedback of pulling or the sight and feel of a hair coming free. While individuals can experience temporary relief, the aftermath may bring distress. The repeated cycle can interfere with school or work, limit social engagement, and contribute to feelings of isolation.
Trichotillomania can occur in people of any gender or age, though it often begins in childhood or adolescence. In children, hair pulling may be brief and resolve spontaneously. In teens and adults, it tends to be more persistent without targeted support. Importantly, trichotillomania is not a sign of laziness or a simple “bad habit.” It is a complex condition driven by biological, psychological, and environmental factors. Understanding that distinction is the first step toward compassion and change.

The Basics of Hair-Pulling Disorder
Hair-pulling disorder (trichotillomania) can affect both hair and scalp health. Repeated traction on hairs can inflame and irritate follicles, especially when pulling is frequent or forceful. In the short term, you might see thinning, broken hairs, or patchy loss. Over a longer period, chronic pulling can lead to scarring in some individuals, reducing the potential for hair regrowth in those areas. The extent of damage varies widely and depends on how often and how intensely pulling occurs, along with individual differences in scalp sensitivity and healing.
In many cases, hair regrowth occurs once traction stops and the follicle remains intact. This regrowth timeline can differ from person to person and from one area of the body to another. Supporting the scalp and hair through gentle care and by addressing the underlying causes of trichotillomania can improve the likelihood of healthy regrowth and help protect follicles from ongoing stress.
The emotional impact is equally significant. People often describe a mixture of relief, shame, and anxiety tied to pulling episodes, which can make them feel stuck in a loop. Social situations may feel risky if bald patches are visible, and self-consciousness can increase the urge to pull for temporary comfort. Effective Treatment for Trichotillomania addresses both behavior and emotion: learning to notice urges earlier, replacing pulling with healthier responses, and strengthening coping skills for stress and uncomfortable sensations.
Trichotillomania vs. Other Compulsive Disorders
Trichotillomania is related to obsessive-compulsive and body-focused repetitive behaviors, yet it differs from classic obsessive-compulsive disorder (OCD). In OCD, unwanted intrusive thoughts (obsessions) typically drive compulsions performed to reduce perceived threats or fears. By contrast, trichotillomania often centers on sensory or emotional regulation rather than fear-based obsessions. Pulling may be sparked by tension, boredom, or a tactile need to “fix” a sensation, and the reward is a brief drop in discomfort rather than the prevention of a feared outcome.
Another difference lies in awareness. Some people engage in automatic pulling with minimal conscious realization until after it occurs, while others perform highly focused pulling and search for specific hairs. Understanding which style fits your experience can shape treatment, as strategies for automatic pulling often focus on environmental changes and competing responses, whereas focused pulling may benefit from skills that interrupt rituals and address perfectionistic or sensory-driven urges.

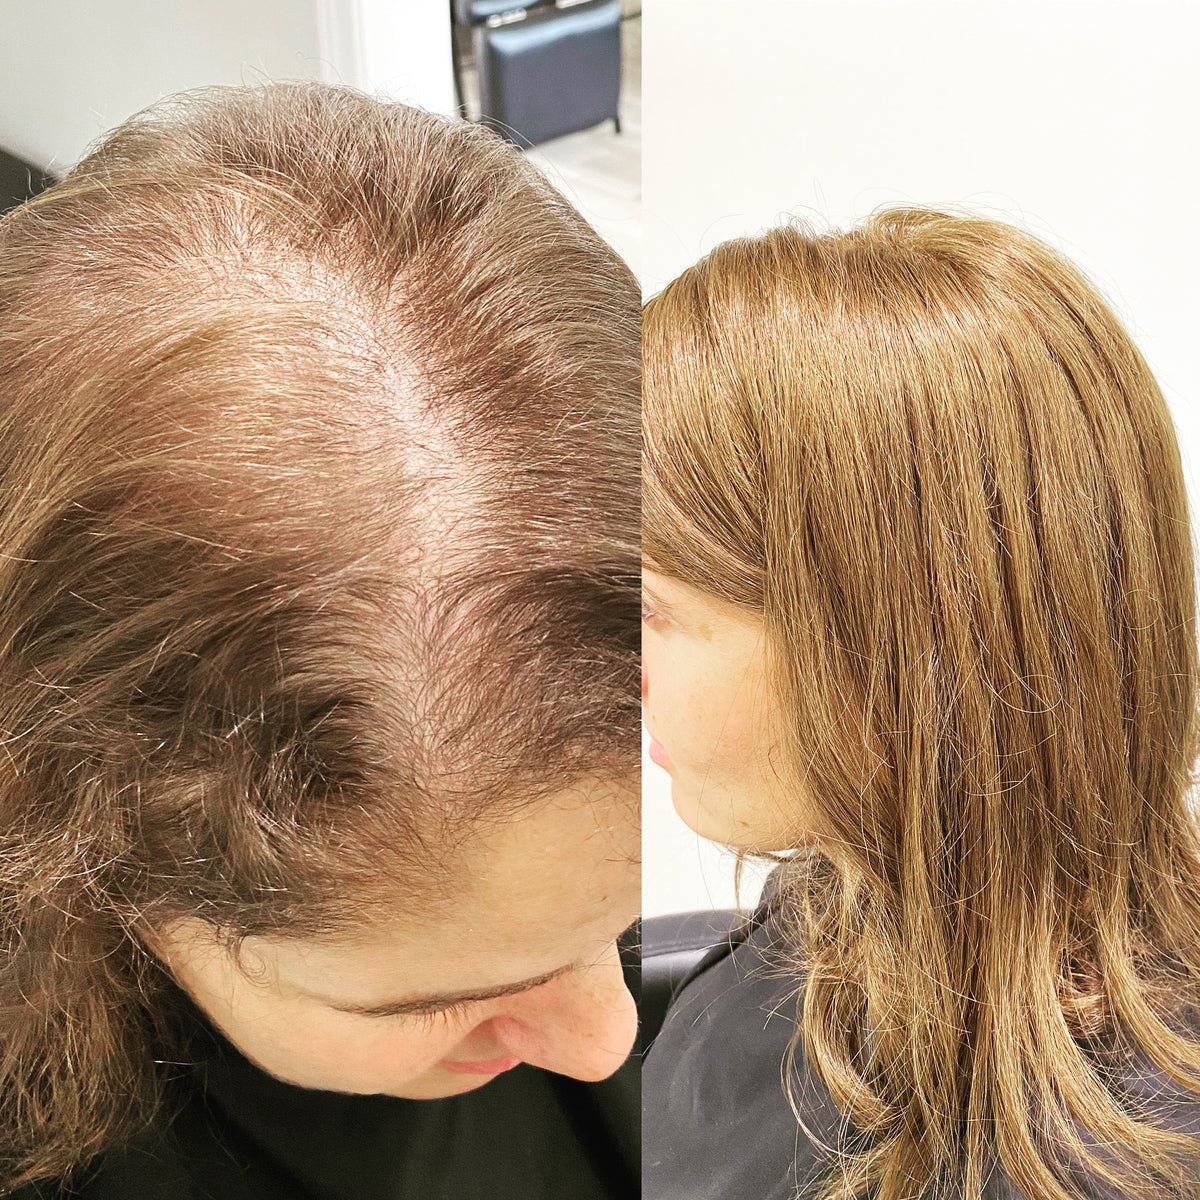
Visible signs of trichotillomania—areas of thinning hair serve as a reminder of the inner turmoil and ongoing battle against compulsive pulling.
The Impact of Trichotillomania on Hair Health
From a hair and scalp perspective, repeated pulling can cause breakage near the root, a ragged hairline, or sparse eyebrows and lashes. Some people notice that hair texture seems different as it grows back, or that certain areas regrow more slowly than others. Because pulling often targets the same sites, localized bald patches may appear, which can be difficult to camouflage and may lead to protective styling or accessories to cover the change in density.
Traction alopecia is a pattern of loss caused by persistent tension on the hair. In trichotillomania, that tension comes from the hand rather than tight hairstyles, but the effect on the follicle can be similar. With ongoing traction, the follicle can become inflamed and fragile, potentially leading to thinning and, in some cases, scarring. Early intervention helps reduce prolonged stress on follicles, improving the odds of regrowth and minimizing lasting changes in hair density.
Comprehensive care pairs behavior change with scalp-friendly habits: gentle cleansing, minimal heat and chemical treatments, and patience as hair moves through normal growth cycles. When pulling eases, many individuals see encouraging signs of regrowth. For others, especially after years of chronic traction, some thinning may persist, and targeted cosmetic or restorative options can help create a fuller look while recovery continues.

How Trichotillomania Leads to Hair Loss
Hair grows from follicles that cycle through growth, rest, and shedding phases. Pulling forcibly removes hairs, disrupting this natural rhythm. When traction is repeated in the same spots, follicles endure inflammation and micro-injury, and the surrounding skin may become tender or irritated. Over time, frequent pulling can reduce the number of actively growing hairs in that region, leading to thinner coverage and visible patches.
Another factor is the feedback loop between sensation and behavior. For some, a prickly or coarse hair triggers the urge to extract it, but extracting increases sensitivity in that spot, making it more likely you will notice and target new hairs there. Interrupting this loop with coping strategies and tactile substitutes helps reduce the mechanical strain on follicles so they can return to healthier growth cycles.
If you are noticing expanding patches or very slow regrowth, consider how often pulling happens during daily routines and add small barriers or reminders to break the chain; combined with professional guidance, these steps can reduce ongoing damage and support recovery.
The Risk of Permanent Hair Loss with Long-Term Trichotillomania
Persistent traction over many years increases the risk of lasting changes. When follicles repeatedly sustain injury, scar tissue can replace healthy follicular structures in some individuals, reducing the capacity for new growth in those areas. This is why chronic, high-frequency pulling can contribute to permanent thinning or patchy areas that do not fully recover, even after behavior improves. Many people experience some permanent bald patches after 2 to 3 decades of hair pulling.
If the hair follicles are permanently damaged, regrowth may not occur in the most affected zones. That does not mean recovery is hopeless. Many people see meaningful cosmetic improvement by combining behavioral therapies with gentle hair care and, when needed, cosmetic or restorative solutions. The earlier you reduce traction, the greater the chance of avoiding permanent hair loss. Consider tracking your progress over weeks and months: What changes in urges do you notice? Which strategies seem to shorten or prevent episodes? These observations guide ongoing adjustments to your plan.
Working with a clinician can help you set realistic expectations about hair density and identify options for areas that are slow to return. Even when some permanent loss has occurred, many individuals regain confidence as they learn skills to manage urges and discover ways to enhance the look and health of remaining hair.

Recovery is possible. These images illustrate the journey of regrowth and healing, reinforcing the importance of seeking help early.
Identifying Trichotillomania
Recognizing trichotillomania can be difficult because many people pull in private or at times when attention is elsewhere, such as while reading or scrolling on a phone. Some individuals become skilled at disguising loss with specific partings, hairstyles, or makeup. Nonetheless, a cluster of signs often emerges: recurrent urges to pull, attempts to stop that do not last, and visible changes in the density of hair, lashes, or brows.
Clinicians commonly use interviews and screening tools to assess symptoms and how they affect daily life. A useful starting point is self-observation. Keep a brief log for a week: When did urges spike? What were you doing? How long did an episode last? Did anything help you stop? These notes can clarify patterns and reveal opportunities for targeted changes. If you notice a strong link to stress, certain locations, or specific sensations, that information becomes a roadmap for behavior therapy.
Habit reversal training (HRT), a structured behavioral therapy, is often recommended. It teaches awareness of early signs and helps you replace pulling with a competing, non-damaging action. Over time, people gain confidence that urges can be managed without resorting to hair pulling. Choosing tools that match your environment—work, commuting, home—makes success more likely.
Common Symptoms and Behaviors
Trichotillomania frequently presents with a combination of behaviors and emotional reactions. You may notice some of the following:
- Compulsive hair pulling: recurrent pulling that leads to thinning, broken hairs, or defined bald patches.
- Tension and relief cycle: intense urges tied to tension or sensory discomfort with brief relief immediately after pulling.
- Loss of control: difficulty reducing or stopping pulling despite a strong desire to change.
- Visible hair loss: areas of reduced density that may prompt camouflaging with hats, scarves, hairstyles, makeup, or wigs.
- Concealment behaviors: efforts to hide evidence of pulling or avoid situations where patches might be noticed.
- Emotional distress: shame, guilt, frustration, or worry about how others might react.
People also report specific “rituals,” such as selecting certain textured hairs, examining the root, or feeling for coarse strands. Paying attention to the rituals you use can help tailor therapy. For example, if mirrors cue pulling, you might adjust where and when you groom; if sensation drives the behavior, grounding techniques and tactile substitutions can help meet that need without harming hair.

Environmental and Genetic Influences
Life transitions and stressors—new schools or jobs, relationship changes, or increased responsibilities—often coincide with a rise in pulling. Environments with long periods of sitting and minimal stimulation can also invite automatic pulling. Adjusting these contexts can reduce risk. For example, altering where you sit to read, setting brief timers to stretch, or wearing tactile reminders can lessen automatic episodes before they spiral.
Genetic influences may increase susceptibility, but genetics alone do not determine outcomes. People with a family history of body-focused repetitive behaviors or related conditions might experience stronger urges or earlier onset. Still, proactive strategies—skill building, structured routines, and supportive environments—can shift the trajectory.
Treatment Options for Trichotillomania
Evidence-based therapies, supportive tools, and, in some cases, medication form a comprehensive approach to managing trichotillomania. The heart of treatment is learning to interrupt the cycle: catching urges earlier, replacing pulling with protective responses, and addressing emotional or sensory drivers so the behavior becomes less compelling. Over time, these skills reduce the frequency and intensity of episodes and protect hair health.
Behavioral therapies—especially habit reversal training (HRT)—are widely considered the frontline treatment. HRT teaches you to notice early warning signs and engage a competing response that is physically incompatible with pulling. It also addresses triggers, designs environmental changes, and builds social support. Many people appreciate that HRT offers practical, immediately usable techniques rather than solely discussing the problem.
Medication may be used to address co-occurring conditions like anxiety or depression, which can intensify urges. Prescribers sometimes consider selective serotonin reuptake inhibitors (SSRIs) or other psychiatric medications based on individual needs. While medication alone is not a cure for trichotillomania, it can be a helpful adjunct when combined with therapy and coping strategies.
- Habit Reversal Training (HRT): learn alternative behaviors to replace hair pulling.
- Cognitive Behavioral Therapy (CBT): address thoughts and feelings linked to pulling.
- Support groups: engage with peers who understand for skills and encouragement.
- Medication: explore pharmacologic options with a clinician when appropriate.
- Mindfulness techniques: reduce stress and increase awareness of urges.
Beyond formal treatment, cultivating day-to-day supports—clear routines, accountability check-ins, and positive reinforcement—reduces the likelihood of relapse. The aim is to create a lifestyle that makes pulling less likely and recovery more sustainable.
Managing Trichotillomania Prioritizing Your Scalp
Managing trichotillomania calls for a dual focus: reducing pulling and maintaining a scalp environment that supports hair regrowth. Pair behavioral change with gentle care—mild shampoos, reduced heat styling, and soft brushes—to minimize further stress on follicles. Avoid tight styles and harsh chemical treatments while regrowth stabilizes.
Coping strategies are most powerful when customized. Many people benefit from “urge surfing,” a mindfulness technique that treats urges as waves that rise, crest, and fall. Others prefer immediate tactile substitutions that satisfy the hands without harming hair. You might also create micro-routines around high-risk moments: placing a fidget tool near the couch, using hand lotion before reading, or wearing a soft headband when you feel vulnerable to pulling.
Social support increases resilience. Ask a trusted person to check in with you during challenging times or to practice competing responses together. Shared problem-solving can uncover simple environmental shifts that make a big difference, such as changing lighting, moving mirrors, or adjusting where you sit during activities that typically precede pulling.
Mindfulness and movement can lower overall stress, making urges less intense. Short breathing exercises, gentle stretching, or brief walks offer a reset. Physical barriers can also help: wearing a hair topper or mesh integration that does not require shaving or gluing can create a protective layer, reduce access to targeted areas, and interrupt the pulling cycle—giving follicles time to recover and encouraging hair growth.
Balanced routines round out care: regular sleep, nourishing meals, hydration, and movement all contribute to steadier energy and mood. While none of these steps alone “cures” trichotillomania, together they form a scaffold that supports change and protects hair health over time.
Coping Strategies for Affected Individuals
Think of coping strategies as a toolkit you refine with practice. Start small, choose a few tools that feel natural, and gradually expand. Consider the ideas below and note which might fit your routines:
- Record triggers: keep a brief journal to spot situations, feelings, or times that lead to pulling.
- Use fidget toys and tactile tools: stress balls, smooth stones, fidget cubes, textured fabrics, or putty during reading, studying, or streaming.
- Physical prompts/barriers: bandages or finger sleeves that remind you to pause; soft headbands or hats to reduce access when urges rise.
- Sensory swaps: apply lotion or essential-oil hand balm to occupy touch and scent; hold a warm mug or a cooling pack for grounding.
- Micro-goals and rewards: celebrate short streaks—an evening, a commute, or a meeting without pulling—to build momentum.
- Self-talk scripts: prepare phrases like “This urge will pass,” “I can ride this wave,” or “I choose my hair, not the pull.”
- Relaxation and structured breaks: brief movement or breathing exercises at predictable intervals to reduce automatic pulling.
Over time, patterns will emerge. You’ll discover which tools help with automatic pulling and which address focused, sensory-driven urges. Keep a short log of wins to reinforce progress.

Possibilities of Hair Regrowth After Trichotillomania
Hair regrowth potential depends on follicle health and the duration and intensity of traction. When follicles remain intact, regrowth often begins as pulling decreases. Because hair cycles through growth and rest phases, visible change may be gradual. Patience is crucial: what you do today—reducing traction and supporting scalp health—sets the stage for fuller growth in the months ahead.
Creating a supportive environment includes gentle cleansing, minimal heat styling, protective accessories, and reduced manipulation. It also means prioritizing consistent behavioral strategies to prevent new pulling episodes. Your plan might combine therapy skills, routines that keep hands engaged during high-risk times, and soothing practices that lower overall stress.
Many individuals see encouraging density returns as they gain traction over urges and sustain new habits. A layered approach—behavioral therapy, thoughtful self-care, and, when indicated, guidance from dermatology—optimizes the chances of recovering coverage in affected areas. If you are looking for guidance on next steps, consider a tailored plan for hair regrowth after trichotillomania aligned with your triggers and routines.
Advanced Hair Restoration Techniques
If certain zones have limited regrowth after behavior has improved, advanced cosmetic or restorative solutions can help you look and feel more like yourself while continuing recovery. These approaches range from minimally invasive options to surgical techniques and can be customized to your hair goals and lifestyle.
|
Hair Systems (Wigs) |
Hair systems, such as wigs or hairpieces, offer immediate and temporary solutions for individuals with hair loss due to trichotillomania. Look for a system that does not require shaving or gluing. The system will help to prevent pulling and make one aware of the pulling habit. |

Conclusion
Trichotillomania can lead to long-term or even permanent hair loss when pulling is intense and ongoing, but many people experience meaningful regrowth once the behavior is reduced and follicles have time to recover. Because repeated pulling can inflame and damage the scalp, early, structured support is key.
Combining behavioral therapies, supportive routines, and—when appropriate—medical guidance can help reduce pulling episodes and protect existing hair. Understanding your triggers and having practical tools ready in the moment makes a real difference in building new patterns over time.
For some individuals, hair toppers can also play a supportive role in this process—creating a gentle barrier that helps reduce access for pulling while restoring a natural, confidence-boosting appearance.
You don’t have to navigate this alone. With the right plan, it’s possible to support both your mental well-being and your hair recovery in a way that feels manageable and sustainable.
👉 Book your free trichotillomania consultation to create a personalized plan designed around your needs, your triggers, and your goals.
Frequently Asked Questions
Can hair regrow after years of trichotillomania?
Hair regrowth after long-standing trichotillomania is possible when follicles remain viable. Recovery depends on individual factors: how long and how often pulling occurred, whether scarring is present, and how consistently urges are managed going forward. Gentle care and reduced traction give follicles the best chance to re-enter growth phases. Work with a clinician to shape a plan and be patient with timelines—progress may be gradual but meaningful when behaviors change. Avoiding new traction and taking periodic breaks from hair accessories that strain the scalp can also help as you heal. With steady practice and support, many people see improved coverage in previously affected areas over time.


